What the Anion Gap Measures
The anion gap is a calculated value that assists clinicians judge an electrolyte imbalance and narrow the differential diagnosis of an acid-base disorder. It reviews major measured serum electrolytes to approximate the amount of unmeasured anions in the blood. In practice, it is a valuable clue for identifying the cause of metabolic acidosis and interpreting broader acid-base status.
The calculation uses common laboratory values, especially serum sodium, serum chloride, and serum bicarbonate. Because sodium is the primary measured cation and chloride plus bicarbonate are the main measured anions, the difference between them reveals the balance of other charged particles in plasma. A rising anion gap may indicate an acid load from organic acids or toxins, while a normal value can still occur in acid-base problems when bicarbonate is lost and chloride rises to compensate.
Learning the anion gap is not just about numbers. It is a diagnostic tool that supports clinical interpretation of systemic acid-base problems. The result must be considered alongside the patient’s symptoms, the blood gas, kidney function, and other findings. In other words, the anion gap is most helpful when used as part of a complete review of the clinical picture rather than as Go to the website a stand-alone answer.
How an Anion Gap Calculator Works
An anion gap calculator automates the math and lowers the chance of computational mistakes in a fast-paced clinical setting. It usually asks for serum sodium, serum chloride, and serum bicarbonate. Some calculators also allow input for potassium and albumin, which can enhance clinical value in select cases. The calculator then provides the anion gap and may also show a corrected anion gap if albumin adjustment is included.
The core idea is clear: if the measured electrolytes do not fully clarify the patient’s acid-base findings, the calculator helps identify whether there are additional acids present. This is most important in suspected anion gap acidosis, where extra acids consume bicarbonate and leave behind unmeasured anions. Because serum bicarbonate may be low in many forms of acidosis, the calculator helps determine whether the pattern is more consistent with a high-gap process or a normal-gap process.
Albumin matters because it is a major unmeasured anion. If albumin is low, the anion gap may appear incorrectly normal or only mildly elevated even when clinically meaningful acidosis is present. Some calculators therefore include albumin correction to enhance accuracy. This is not a minor detail; it can alter how you interpret a borderline result, especially in patients with chronic illness, poor nutrition, liver disease, or inflammation.
Although potassium is not always included in standard formulas, some clinicians prefer versions that account for it. Potassium contributes to a smaller extent than sodium, chloride, and bicarbonate in most routine calculations, but including it can slightly alter the result. The key is uniformity: use the same formula when comparing trends, and interpret changes within the broader diagnostic context.
Anion Gap Formula and Reference Ranges
The typical anion gap formula is:
Anion gap = sodium - (chloride + bicarbonate)
When potassium is included, the formula changes to:
Anion gap = sodium + potassium - (chloride + bicarbonate)
Because multiple laboratories and calculators may use varying conventions, the reference range can change. That variability is one reason a reported result should consistently be interpreted according to the specific laboratory method and the patient’s overall condition. A “normal” result on one system may differ slightly from another, so the normal anion gap is best understood as a technique-dependent range rather than a one universal number.
Most clinicians look at whether the anion gap is elevated, normal, or low versus the expected reference range. A above-normal gap often points toward accumulation of unmeasured acids. A normal value does not exclude acidosis, because many acid-base disorders lower bicarbonate while increasing chloride enough to keep the gap unchanged. That pattern is central to recognizing normal anion gap metabolic acidosis.
Albumin correction should be considered when albumin is abnormal, especially if the value is low. Since albumin is a major contributor to the gap, low albumin can mask a clinically significant acid burden. In practice, the corrected result may show a more accurate picture of the patient’s true acid-base status and prevent missed recognition of a high-gap process.
Increased Anion Gap Acidification Causes
This condition develops when acids accumulate and deplete bicarbonate, leaving unmeasured anions behind. This is a frequent form of systemic acidemia and often suggests a major underlying problem that requires prompt evaluation. The major causes include lactic acid accumulation, ketone-related acidosis, and kidney-related toxin buildup, among others.
Elevated lactate occurs when lactate production exceeds clearance, often in settings of tissue hypoperfusion, severe infection, seizures, hypoxemia, or impaired metabolism. Because lactate is an unmeasured anion, its buildup elevates the anion gap and promotes systemic acidemia. In such cases, the calculator result can reinforce the suspicion of shock, poor perfusion, or another major physiologic stressor.
Ketone accumulation occurs when ketone production rises substantially, as in diabetic ketoacidosis, alcoholic ketoacidosis, or starvation states. Ketones act as unmeasured acids and increase the gap. Here, the anion gap calculator can be useful for trend monitoring, helping clinicians assess whether treatment is closing the gap as the metabolic derangement improves.
Advanced kidney dysfunction from advanced kidney dysfunction is another classic cause. With impaired renal function, acids are not excreted normally, and retained organic acids contribute to the elevated gap. The result may reflect both reduced clearance of acids and accumulation of other metabolites. In this setting, the calculator assists with recognition of kidney-related acid retention, but it should always be paired with renal studies and the clinical presentation.
Normal Anion Gap Metabolic Acidosis Causes
Normal anion-gap metabolic acidosis is commonly referred to as hyperchloremic acidosis because chloride rises as bicarbonate falls, maintaining the calculated gap. This pattern can be equally clinically significant as a high-gap disorder, even though the calculator does not show an elevated value. The main concept is bicarbonate depletion or failure to regenerate bicarbonate, rather than accumulation of unmeasured acids.
Diarrhea is a frequent cause because the gastrointestinal tract can lose large amounts of bicarbonate-rich fluid. As bicarbonate drops, the body retains chloride to maintain electroneutrality, and the gap remains in the normal range. This is a classic example of why a normal result does not rule out acidosis.
Renal tubular acidosis is another major cause. In this disorder, the kidneys fail to properly handle acid excretion or bicarbonate conservation, leading to persistent metabolic acidosis with a normal gap. The patient may have a fairly subtle presentation, which makes laboratory pattern recognition essential. An anion gap calculator helps separate this from high-gap conditions that require different urgent responses.
Other causes also fit this pattern, but the central concept is the same: bicarbonate loss or impaired acid handling without major accumulation of unmeasured anions. Recognizing this helps avoid mislabeling the disorder and supports a more precise differential diagnosis.
How to Read Results in a Clinical Context
The anion gap should under no circumstances be interpreted in isolation alone. A meaningful assessment includes the blood gas, pH, serum chloride, bicarbonate, and the broader clinical picture. A low bicarbonate alone does not separate between high-gap and normal-gap acidosis. The pH tells you whether the patient has systemic acidemia, while the anion gap helps explain the likely mechanism.
If the blood gas shows acidemia and the anion gap is elevated, the pattern strongly supports a high-gap process such as lactic acidosis, ketoacidosis, or uremia. If the pH is low but the gap is normal, consider diarrhea, renal tubular acidosis, or another hyperchloremic process. The serum chloride is very helpful here because a rise in serum chloride often accompanies loss of bicarbonate in normal-gap states.
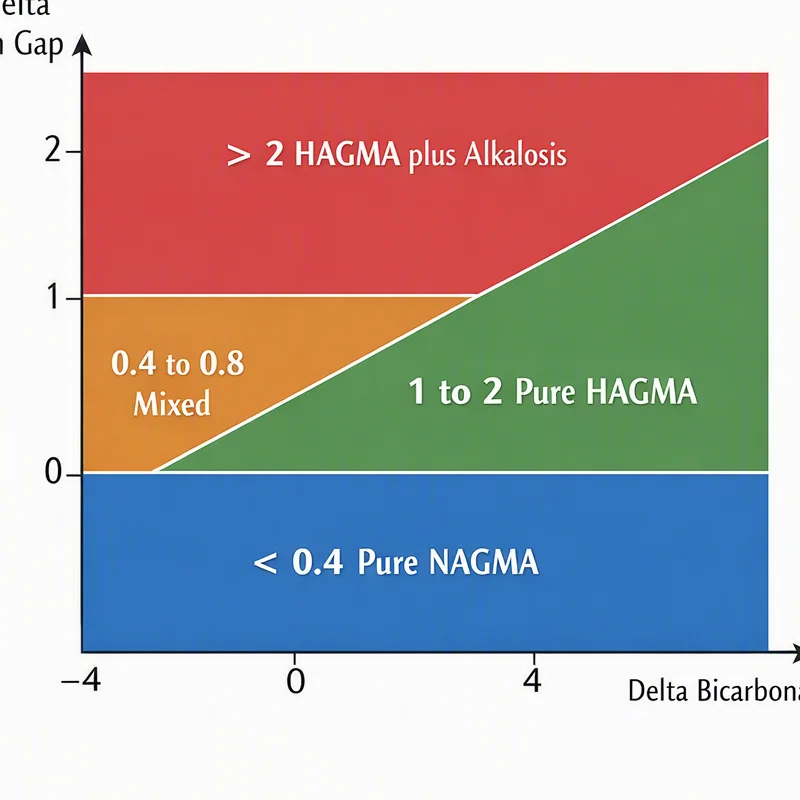
The delta gap can help detect a mixed acid-base disorder. This approach compares the rise in anion gap to the fall in bicarbonate. If the gap increase is much larger or smaller than expected, another acid-base process may be present at the same time. For example, a patient may have a high-gap acidosis plus a metabolic alkalosis, or a high-gap acidosis plus an additional normal-gap component. That is why the calculator result should be viewed in interpretive context rather than as a single, straightforward yes-or-no answer.
In practice, the best use of the calculator is pattern recognition. Ask whether the result matches the blood gas, the clinical scenario, and the likely source of the acid-base problem. This approach improves diagnostic accuracy and helps inform timely next steps.
Typical Pitfalls and Constraints
A number of pitfalls can skew interpretation. Hypoalbuminemia is one of the most significant because it reduces the measured gap and can conceal a meaningful high-gap process. Without albumin correction, a patient with true acid burden may appear to have a near-normal result. This is a common reason for minimizing the severity of acidosis.
Laboratory error is another issue. A single abnormal value may suggest sample handling problems, contamination, or an analytic problem rather than true physiology. When the number does not fit the clinical picture, repeat testing and review of the specimen and methods may be warranted. Because the anion gap is derived from other values, an error in sodium, chloride, or bicarbonate can shift the final result substantially.
Measurement variability across laboratories can also affect the reference range and the interpretation of borderline cases. Different analyzers may report slightly different values, especially for bicarbonate or chloride. In addition, a mixed acid-base disorder can partially disguise the expected pattern and make the gap appear less obvious than it truly is. These limitations do not diminish the usefulness of the calculator, but they do reinforce the need for thorough clinical interpretation.
Finally, a normal result does not exclude disease. The calculator is best used as a structured aid to recognize likely patterns, not as a substitute for the full clinical assessment. That is especially true when the patient has complex illness, fluctuating renal function, or multiple simultaneous metabolic derangements.
When to Obtain Prompt Medical Evaluation
The condition can turn dangerous fast, particularly when it is severe or accompanied by worsening symptoms. Get urgent medical attention if there are signs of severe acidosis or an abrupt decline in condition. Concerning symptoms may include deep or rapid breathing, profound weakness, vomiting, chest discomfort, marked fatigue, or inability to stay awake.
Confusion is very important because it may signal worsening acidemia, poor perfusion, infection, toxic exposure, or another serious cause of metabolic derangement. Respiratory distress is also a warning sign, since the body may be trying to compensate for acidosis by increasing ventilation. If breathing becomes labored, the patient is not compensating adequately or the underlying problem may be worsening.
An anion gap calculator can help detect a worrisome pattern, but it should not delay care when the patient appears unstable. If the lab pattern and clinical presentation suggest severe illness, urgent evaluation is appropriate even before all confirmatory testing is complete.
FAQ
What is an anion gap calculator used for?
An anion gap calculator is used to calculate the anion gap from common serum electrolytes and help assess the cause of acidosis. It supports recognition of high anion gap metabolic acidosis, normal anion gap metabolic acidosis, and possible mixed disorders. It is a practical diagnostic tool for clinical interpretation, especially when paired with blood gas results and other laboratory values.
What does a high anion gap mean in acidosis?
A high anion gap in acidosis usually means there are additional unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, and uremia. In this setting, the calculator suggests that bicarbonate has been consumed by acid load, which helps refine the differential diagnosis and identify the likely source of the metabolic acidosis.
How do you correct the anion gap for albumin?
Correcting for albumin adjusts the anion gap up when albumin is low, because albumin is a key unmeasured anion. The specific correction method can vary by formula, but the basic idea is to account for the hidden contribution of low albumin so the corrected anion gap better reflects true acid-base status. This is especially useful when hypoalbuminemia may obscure a increased-gap disorder.
What causes a normal anion gap metabolic acidosis?
Normal anion gap metabolic acidosis is often caused by diarrhea, renal tubular acidosis, and other forms of bicarbonate loss or impaired bicarbonate handling. In these cases, chloride tends to rise as bicarbonate falls, so the gap remains within the reference range even though acidosis is present. That is why a normal result does not exclude clinically important acid-base disease.
Can the anion gap be normal even when acidosis is present?
Yes, it can. Acidosis can be present with a normal anion gap, especially in normal anion gap metabolic acidosis due to diarrhea or renal tubular acidosis. This is why the anion gap calculator should be interpreted alongside pH, blood gas findings, serum chloride, and the overall clinical picture. Albumin correction may also reveal a hidden high-gap process when the uncorrected value appears normal.