How the Anion Gap Is Assessed
The anion gap is a helpful way to interpret serum chemistry values and gauge the difference between measured cations and measured anions in the body. It is most often used alongside an electrolyte panel to help identify an electrolyte imbalance or an underlying acid-base disorder. While it is not a diagnosis by itself, it is a valuable screening tool for clinical assessment and patient evaluation.
In simple terms, the anion gap reflects the gap between the positively charged and negatively charged components that are routinely measured in serum electrolytes. The main values involved are sodium, chloride, and bicarbonate, with potassium sometimes included depending on the formula used. Because many important acids are not directly measured in routine testing, the anion gap helps suggest the presence of unmeasured anions that may be contributing to a metabolic disturbance.
Clinically, this measurement has significant significance in the evaluation of metabolic acidosis. It can point toward a wide differential diagnosis, especially when paired with a blood gas and the rest of the serum chemistry profile. Used correctly, it supports diagnostic reasoning rather than replacing it.
How to Use an Anion Gap Calculator
An Anion Gap Calculator provides a fast calculation using routinely reported serum values. Input the patient’s sodium, chloride, and bicarbonate from the laboratory result, and the calculator yields the anion gap. Some calculators also include inclusion of potassium, though the standard approach often omits it for simplicity and uniformity with many clinical workflows.
The basic process is straightforward:
- Review the patient’s electrolyte panel and ensure the relevant serum values. Enter sodium, chloride, and bicarbonate into the calculator. Assess the calculated result in the context of the clinical presentation. Determine whether albumin may require an adjustment. Use the result as part of broader interpretation, not as a stand-alone answer.
This calculation can be particularly helpful when assessing whether a metabolic disturbance is consistent with high anion gap metabolic acidosis or normal anion gap metabolic acidosis. In practice, the number is only one part of the analysis. The real value of the calculator is in helping clinicians quickly connect chemistry data to acid-base balance and the likely mechanism of disease.
Because the calculation is based on routine serum values, the quality of the input matters. If there is a measurement issue, missing data, or a specimen concern, the output may be misleading. A calculator is a screening tool, but the interpretation still depends on clinical judgment.
Anion Gap Formula and Normal Range
The standard anion gap formula is:
Anion gap = sodium − (chloride + bicarbonate)
Some clinicians include potassium in the equation, but the simplified version above is commonly used because potassium adds little to the total outcome. No matter the exact formula, the goal is the same: to assess the difference between measured ions and infer the presence of unmeasured anions.
The normal anion gap depends on the laboratory and the method used, so it is important to check the local reference range. A reported result should always be compared with the range provided by the lab rather than assumed to be normal or abnormal based on a single universal cutoff. Differences in analyzer technology, reporting conventions, and whether potassium is included can all influence the expected interval.
Because of this variability, clinicians should evaluate the result as part of the broader serum chemistry profile. The most useful approach is to compare the calculated gap with the lab’s reference range, then decide whether the result is elevated, decreased, or within expected limits. That interpretation has direct clinical significance in acid-base analysis.
Reasons of a High Anion Gap
A increased anion gap metabolic acidosis points to the accumulation of acids that are not directly measured in routine serum chemistry. This finding often indicates that the body is retaining excess acid, using up bicarbonate in the process and leaving behind undetected anions. The result is a unexpectedly high calculated gap.
One common cause is an accumulation of lactate, in which lactate rises during tissue hypoperfusion, severe illness, hypoxia, or other metabolic stress. Another important cause is a ketone-driven acidosis, which may occur in diabetes, starvation, or alcohol-related metabolic disturbance. In these settings, ketone bodies add to the elevated gap and the associated acid-base disorder.
Renal failure is also a classic cause. As kidney function declines, the body becomes less able to clear acids efficiently, and retained solutes play a role in the widening gap. Other causes may exist, but these three are among the most clinically important because they are common and often urgent.
When the anion gap is elevated, interpretation should focus on the context of the patient’s symptoms, serum values, and blood gas findings. The calculator helps confirm the presence of a metabolic pattern, but the differential diagnosis still depends on the overall clinical picture. An elevated gap is a clue to look for a significant acid load, impaired clearance, or both.
Reasons of a Expected or Reduced Anion Gap
A normal anion gap metabolic acidosis can still indicate a real acid-base problem, even though the calculated gap is not elevated. In these cases, bicarbonate is usually consumed, and chloride rises to maintain electrical neutrality. This pattern is often called hyperchloremic metabolic acidosis and may occur with gastrointestinal bicarbonate loss, renal tubular problems, or certain medication effects.
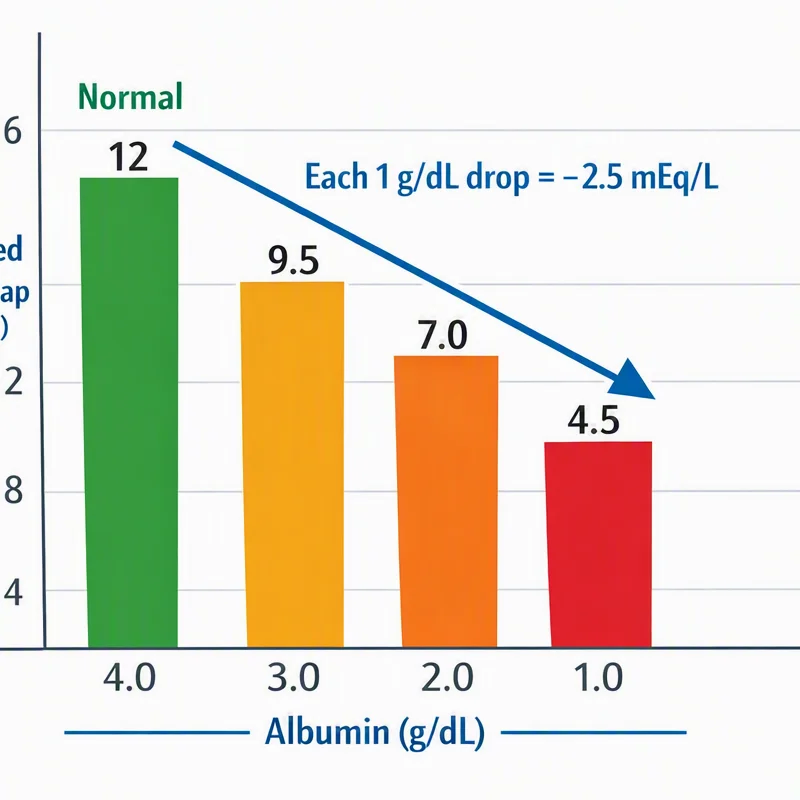
A unexpectedly low result may also occur with hypoalbuminemia. Because albumin carries negative charge, a reduction in albumin lowers the measured gap. This is one of the most important reasons not to overread a low or normal value without checking protein status and considering a correction.
Paraproteinemia can also change the result. In some plasma cell disorders, positively charged proteins affect with the balance of measured ions and can reduce the observed gap. This makes the interpretation harder and increases the need for a careful differential diagnosis.
Other contributors may include laboratory issues, unusual ion composition, or specific medications. The key point is that a normal or low value does not automatically exclude metabolic acidosis. It may instead point to a different pattern of acid-base balance or to a factor that is masking the true burden of acid.
Correcting Albumin and Why It Matters
Albumin correction is essential when assessing the anion gap in patients with low protein levels. Because serum albumin is a primary unmeasured anion, a decrease in albumin can cause the calculated gap appear falsely normal or only mildly elevated. Put differently, the raw number may downplay the true acid burden.
The corrected anion gap updates the measured value upward based on the degree of hypoalbuminemia. This adjustment enhances clinical assessment and helps avoid missing a high-gap process in patients whose albumin is decreased. The exact adjustment method may vary by institution, but the principle is consistent: lower albumin means a lower baseline gap, so the measured result should be interpreted in light of that change.
This matters most in patients with advanced illness, malnutrition, liver disease, nephrotic-range protein loss, or other states associated with low albumin. In those situations, a seemingly normal serum chemistry result may hide a important metabolic disturbance. Albumin correction is therefore not a minor technical detail; it is a key part of reliable interpretation.
For practical use, the calculator output should be checked together with lactic acidosis AG monitoring the albumin level whenever available. If albumin is low, the adjusted interpretation may reveal a more clinically important acid-base disorder than the uncorrected value suggests.
Physiologic Interpretation in Acid-Base Disorders
The anion gap is most helpful when incorporated into the overall assessment of acid-base imbalances. A patient with metabolic acidemia should be assessed using the serum chemistry, the blood gas, and the overall presentation. The gap helps differentiate between findings that suggest acid accumulation and patterns that suggest bicarbonate reduction with adaptive chloride retention.
A blood gas supplies important information about pH, carbon dioxide, and respiratory compensation. Along with with serum electrolytes, it helps determine whether the primary problem is metabolic, respiratory, or mixed. In this setting, the anion gap is a diagnostic bridge between the chemistry panel and the physiologic response.
For example, a patient with a reduced bicarbonate and elevated gap likely has a high anion gap metabolic process such as lactic acidosis or ketoacidosis. A patient with low bicarbonate but a normal gap may have a normal anion gap acidosis instead. That distinction changes the evaluation path and often the urgency of treatment.
Clinical significance also depends on whether the result is stable, deteriorating, or changing after treatment. Serial measurements can help track response and support patient evaluation over time. The calculation is not only about identifying a problem; it is also useful for monitoring a known metabolic disturbance.
Typical Calculation Mistakes and Traps
Still a helpful formula can deceive if the base test values are imprecise or partial. Testing error is one of the commonest pitfalls. A blood sample that is damaged, polluted, delayed, or otherwise compromised can affect serum values and distort the end result.
A further common issue is failing to remember that the gap reflects only measured ions. Important contributors may be hidden as hidden anions, so a apparently normal value does not always mean the chemistry is reassuring. The interpretation must include the possibility of combined disorders, unusual toxins, or changing physiology.
Clinicians should also be careful about uneven use of the formula. If a calculator includes potassium while another does not, the result may change somewhat. That is not necessarily an error, but it does mean the stated value must be interpreted according to the exact formula used. Likewise, the reference range should be taken from the same laboratory that produced the result.
In the end, it is important not to treat the calculator output as conclusive on its own. An anion gap is a first step for analysis, not the final diagnosis. If the clinical picture and the serum chemistry do not match, the discrepancy should prompt a closer review of the patient’s acid-base balance, medications, renal function, and overall presentation.
Frequently Asked Questions About Anion Gap Interpretation
What is the anion gap in serum chemistry?
The anion gap is a computed value from blood chemistry that helps assess the balance between measured cations and anions. It is commonly used to assess acid-base balance, identify metabolic acidosis, and look for the presence of nonmeasured anions that are not listed on a routine electrolyte panel.
How do you calculate the anion gap?
The usual formula is sodium minus the sum of chloride and bicarbonate. Some formulas also include potassium, but many clinical settings use the simplified version. An Anion Gap Calculator does this calculation instantly from the reported serum values.
What is the meaning of a high anion gap?
A high result typically points to high anion gap metabolic acidosis, which means acids are building up in the body. Common causes include lactic acidosis, ketoacidosis, and renal failure. The finding should be interpreted alongside the blood gas, symptoms, and other laboratory data.
Why do you correct the anion gap for albumin?
You correct it because albumin is a major unmeasured anion. When hypoalbuminemia is present, the measured gap may seem falsely low or normal. Albumin correction helps show the more accurate corrected anion gap and improves clinical interpretation.
Can a normal anion gap still indicate metabolic acidosis?
Yes. A normal anion gap metabolic acidosis is a real acid-base disorder and does not rule out acidosis. It often reflects bicarbonate loss with compensatory chloride increase. The full assessment should include serum electrolytes, blood gas analysis, and the clinical context.