What Is the Anion Gap?
The anion gap is a measure used in acid-base interpretation anion gap in chronic kidney disease to assess the amount of unmeasured anions in the blood. It is usually derived from common serum electrolytes, especially sodium, chloride, and bicarbonate. In simple terms, the anion gap calculator helps clinicians determine whether there are additional acids in the bloodstream that are not directly measured on a basic metabolic panel.
Most of the time, the formula is based on sodium minus chloride and bicarbonate. Because sodium is the main measured cation and chloride and bicarbonate are the main measured anions, the gap reflects the difference between what is measured and what is not. A above-normal result suggests an elevated anion gap, which often points to acid accumulation from conditions that produce organic acids or other unmeasured acid load.
This matters because the anion gap is not a diagnosis by itself. It is a pattern. A high value prompts a search for causes of high anion gap metabolic acidosis, but the result must always be interpreted with the rest of the clinical picture, including serum bicarbonate, pH, and the patient’s symptoms.
Albumin is especially important because it is a major unmeasured anion. If albumin is low, the anion gap may appear falsely normal. That is why an albumin-corrected anion gap is often more informative than the raw number. This type of gap correction helps support laboratory interpretation and avoids missing clinically important acidosis.
How Methanol Causes High Anion Gap Metabolic Acidosis
The direct answer is yes: methanol can cause high anion gap In methanol poisoning, the original compound isn't the main acid problem early on. Instead of that, methanol is metabolized into formic acid, which is poisonous and drives metabolic acidosis. When formic acid accumulates, the body’s acid-base balance shifts toward systemic acidosis, and the anion gap rises because those acids are not directly measured by routine labs.
For this reason methanol is one of the classic toxic alcohols associated with an sodium chloride bicarbonate anion gap formula elevated anion gap. The process begins after toxic ingestion or other exposure, when alcohol dehydrogenase converts methanol into formaldehyde and then to formic acid. Formic acid is the primary factor of the metabolic derangement. As it builds up, it depletes bicarbonate, lowering bicarbonate and producing a high anion gap state.
This biochemical process also explains why symptoms may be delayed. Early after ingestion, the anion gap may not be very high yet, especially if methanol has not been fully metabolized. Later, as more formic acid accumulates, the gap often rises and acidosis becomes more obvious. This timeline is important for clinical suspicion and for deciding when to pursue a full diagnostic workup.
Methanol toxicity also causes characteristic end-organ effects. Because formic acid is especially harmful to the optic nerve and retina, patients may develop visual disturbances, blurred vision, or other signs of ocular toxicity. These features, combined with acid-base abnormalities, create a strong concern for a toxic ingestion that requires emergency attention.
How to Read an Anion Gap Calculator Value
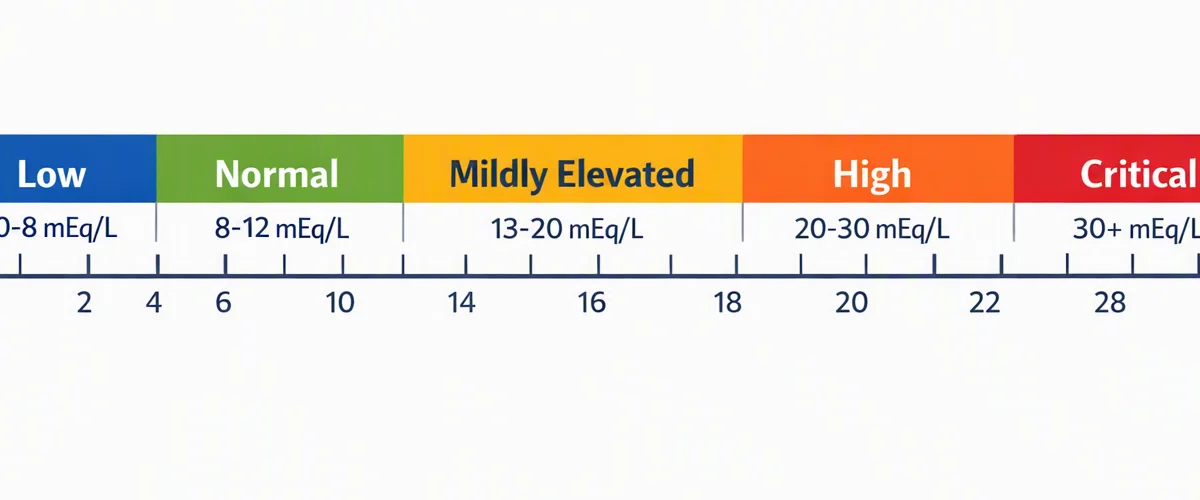
An anion gap calculator is valuable, but the result should never be read in isolation. A “normal” value does not necessarily mean there is no toxic alcohol exposure, and a high value does not prove methanol. The first step is to compare the result with the expected range used by the lab and then evaluate whether the patient has metabolic acidosis as shown by low bicarbonate, low pH, or both.
A normal anion gap suggests there is no obvious accumulation of unmeasured acids at that moment, but it does not exclude early methanol exposure. If the patient presents early after ingestion, serum methanol may still be present before significant formic acid production. In that setting, the osmolar gap may be more helpful initially, while the anion gap rises later as metabolism progresses.
Albumin must be considered in any serious interpretation. Low albumin lowers the baseline gap, so a patient with substantial acid load can appear deceptively normal. Using an albumin-corrected anion gap can expose an abnormality that the uncorrected calculation misses. This is a key point in sound acid-base interpretation and should be part of every thoughtful review of serum electrolytes.
There are also practical nuances:
- A rising gap over time is often more concerning than a single snapshot. Low bicarbonate with a modest gap may still suggest significant acid-base disease. Mixed disorders can confuse the picture, especially in critically ill patients. Clinical context counts more than the calculator alone.
In short, the anion gap calculator is a screening and interpretation tool. It helps identify whether there are unmeasured anions consistent with toxic ingestion, lactic acid production, or another cause of metabolic derangement, but it should be paired with blood gas analysis, osmolality, and bedside assessment.
Common Lab Findings in Methanol Toxicity
Several test results frequently appear together in methanol toxicity. One especially important finding is an elevated osmolar gap early in the course. This reflects the presence of unmeasured osmotic substances, including methanol itself. As metabolism goes on, the osmolar gap may drop while the anion gap goes up, because the parent alcohol is converted into acidic metabolites.
An arterial blood gas is important for assessing severity. It can indicate the degree of acidemia, the respiratory compensation, and whether there is a mixed disorder. In methanol poisoning, blood gas analysis often reveals metabolic acidosis with a low pH and reduced bicarbonate. The pattern may be pronounced, especially if diagnosis is delayed.
Lactate can be elevated as well, but it should not take away from the main diagnosis. Sometimes a true secondary lactic acidosis develops from tissue hypoxia, shock, or poor perfusion. In other cases, lab artifacts or overlapping illness cloud the picture. Either way, lactate does not prove or dismiss methanol by itself.
Bicarbonate is often low because it is depleted buffering the acid load. The drop in bicarbonate is one of the reasons the anion gap rises. In severe cases, serum bicarbonate can be profoundly depressed, reflecting major systemic acidosis and the need for urgent treatment.
Additional useful findings are:
- High serum osmolality or an increased osmolar gap Decreased pH on blood gas analysis Electrolyte abnormalities that affect acid-base interpretation Signs of end-organ injury, including neurologic symptoms or ocular toxicity
When the laboratory pattern is consistent, methanol should remain high on the differential, especially if there is concern for toxic ingestion and the patient shows worsening metabolic derangement.
Differential Diagnosis of High Anion Gap Metabolic Acidosis
Even though methanol is a classic cause, it is only one part of the wider differential diagnosis of high anion gap metabolic acidosis. A number of other conditions can create the same pattern, and close comparison helps avoid diagnostic error. The most common alternatives include lactic acidosis, ketoacidosis, and uremia.
Lactic acidosis is often seen in sepsis, shock, hypoxia, seizures, or severe tissue hypoperfusion. It can produce a high anion gap because lactate is an unmeasured anion. In many patients, it is the leading explanation for metabolic acidosis in the hospital setting.
Ketoacidosis occurs in diabetic ketoacidosis, alcoholic ketoacidosis, and starvation states. Ketone bodies act as unmeasured acids and raise the gap. The clinical context, glucose level, and ketone testing help distinguish ketoacidosis from toxic alcohol exposure.
Uremia from kidney failure can also produce a high anion gap. When the kidneys cannot clear acid effectively, multiple retained solutes contribute to the gap. Because renal failure can coexist with other illnesses, it may blur or overlap with toxic ingestion.
Ethylene glycol is another critical toxic alcohol in the differential. It often causes high anion gap metabolic acidosis as well, and the distinction matters because treatment and complications differ. Ethylene glycol may also cause kidney injury and crystal formation, while methanol more strongly raises concern for visual injury.
In real-world settings, the differential diagnosis should be organized by the clinical picture, the osmolar gap, blood gas findings, ketones, kidney function, and exposure history. No single value replaces thoughtful acid-base interpretation.
When Methanol Should Be Suspected
Suspicion of methanol should arise when a patient has acidosis without a clear cause plus a relevant exposure history or set of symptoms. The most important clue is a history of ingestion or possible contact with adulterated alcohol or industrial products. Because patients may not always give a clear history, the clinician must often rely on indirect signs.
Signs of methanol exposure include visual symptoms such as impaired vision, “snowfield” vision, or loss of sharpness. These findings are highly concerning because they point toward formic acid toxicity and possible ocular injury. The presence of neurologic symptoms such as headache, confusion, ataxia, or declining mental status also increases suspicion.
Central nervous system depression can occur in severe poisoning and should be treated as an emergency. A patient may appear intoxicated, but the severity of the acidosis is often out of proportion to a simple ethanol effect. That mismatch is one reason methanol and other toxic alcohols deserve immediate consideration.
Other clues include:
- Unexplained elevated anion gap with low bicarbonate Elevated osmolar gap in the right setting Progressive worsening after an apparent delay Possible exposure from a toxic ingestion
Because the presentation can be nonspecific at first, methanol is often a diagnosis of clinical suspicion supported by laboratory evidence. Early recognition is key to preventing severe acidosis, vision loss, and organ failure.
Treatment Overview
Treatment of methanol poisoning is time-sensitive and should begin as soon as the diagnosis is suspected. The primary antidotal treatment is fomepizole, which inhibits alcohol dehydrogenase and keeps methanol from being converted into formic acid. By stopping this metabolic pathway, fomepizole helps limit worsening acidosis and toxic metabolite formation.
Hemodialysis may be needed when acidosis is marked, methanol levels are high, visual symptoms are present, or the patient is clinically unstable. Dialysis removes methanol and formic acid directly and also helps restore acid-base abnormalities. It is a key intervention in severe poisonings and is often used together with the antidote.
Sodium bicarbonate is frequently used to help treat severe acidosis and support acid-base balance. It does not remove the toxin, but it can short-term improve pH while definitive therapy is arranged. The decision to give bicarbonate depends on severity, pH, and the full clinical situation.
Supportive care remains essential. This includes airway management if needed, monitoring of electrolytes and blood gas values, treatment of complications, and careful reassessment. Because patients can deteriorate quickly, methanol poisoning is an emergency evaluation scenario rather than a observe-only problem.
Overall, treatment aims to stop toxic metabolism, remove the poison, and stabilize the patient while the diagnostic workup continues.
Frequently Asked Questions: Methanol and Anion Gap
Can methanol trigger a high anion gap?
Yes. Methanol can result in a raised anion gap because it is broken down into formic acid, which causes high anion gap metabolic acidosis. The elevation in the gap reflects unmeasured acids collecting in the blood as bicarbonate decreases.
How does methanol toxicity elevate the anion gap?
Methanol toxicity raises the anion gap because the body converts methanol into formic acid, an acid that is not typically measured on routine chemistry panels. As acid builds up, bicarbonate is used up and the gap rises. This is a classic example of acid accumulation and systemic acidosis in toxic ingestion.
What is the difference between an anion gap and an osmolar gap?
The anion gap reflects unmeasured anions and can help identify metabolic acidosis. The osmolar gap reflects unmeasured osmoles in the blood and is often raised early in toxic alcohol exposure. In methanol poisoning, the osmolar gap may be raised initially, then the anion gap increases later as methanol is converted to formic acid.
Can a normal anion gap rule out methanol poisoning?
No. A normal anion gap does not rule out methanol poisoning, especially early after ingestion or when albumin is low. The patient may still have methanol in the blood before enough formic acid has formed. That is why clinicians also rely on osmolar gap, arterial blood gas findings, symptoms, and overall clinical suspicion.
What lab tests are most useful when methanol ingestion is suspected?
The most useful tests include serum electrolytes, bicarbonate, albumin for gap correction, anion gap calculator output, osmolar gap assessment, arterial blood gas, lactate, serum osmolality, and toxicology-related testing when available. These results support diagnosis, guide acid-base interpretation, and help distinguish methanol from lactic acidosis, ketoacidosis, ethylene glycol exposure, and other causes of metabolic acidosis.