The anion gap is a practical tool for reviewing acid-base imbalances, but its result is not constant. It can vary with the lab method, the electrolyte analyzer, and the particular measurement technique used by the laboratory. That is the reason the same blood sample can yield slightly different results depending on the platform, the specimen type, and the laboratory reporting standards. An Anion Gap Calculator is helpful, but it should be used with awareness of analytical variation and the local reference interval.
In real-world serum chemistry, the anion gap is not just a measurement. It reflects sodium concentration, serum chloride, and serum bicarbonate, all of which can shift with instrument calibration, assay design, and preanalytic factors. Because of this, the result may be method-dependent, and the clinical significance depends on whether the change affects interpretation in the context of the patient’s acid-base status.
What Is the Anion Gap and How Is It Computed?
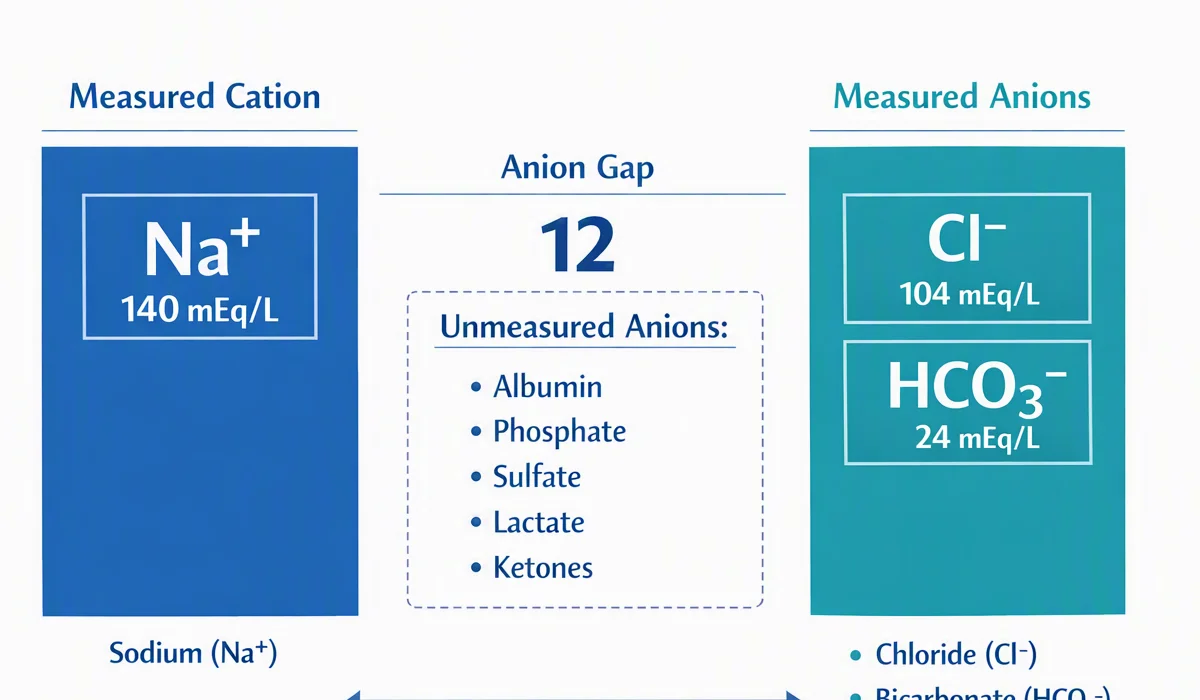
The anion gap is a derived value that approximates the difference between measured cations and anions in blood. The standard calculation formula is:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
This formula uses serum sodium, serum chloride, and serum bicarbonate, usually reported in mEq/L. Some laboratories also calculate a version that includes potassium, but the sodium-based version is the standard in clinical practice and in most Anion Gap Calculator tools.
The result is interpreted as a rough estimate of unmeasured ions. A higher value can suggest build-up of acids, while a lower value may reflect low albumin, lab-related bias, or other factors. Because the anion gap is calculated rather than directly measured, any small shift in one input can change the output. That makes the calculation sensitive to both biological variation and analytical variation.
The key point is that the anion gap is not a standalone diagnosis. It is a screening and interpretation tool that supports evaluation of acid-base disorders, especially when paired with other serum chemistry results and the clinical picture.
Can the Anion Gap Change With Lab Method?
Absolutely, the anion gap can change with lab method. Different laboratories may use distinct analyzers, different electrolyte measurement techniques, and different reporting conventions. Even when the same blood sample is tested, small differences in sodium, chloride, or bicarbonate can produce a altered calculated gap.
The primary source of variation is the electrolyte analyzer and how it measures ions. Modern instruments are exact, but not identical. That means the same patient can have mildly different results across platforms because of assay design, calibration, and assay variability. These differences are often minor, but they can matter when the anion gap is near the upper or lower edge of the laboratory reference range.
From a clinical interpretation standpoint, the question is not whether every result changes substantially. It is whether the method-related shift is significant enough to change the diagnostic conclusion. In some cases, a difference of a few mEq/L does not matter. In others, it can affect whether the clinician suspects an elevated gap metabolic acidosis, a corrected gap, or a normal result.
Why Multiple Analytical Methods Influence the Outcome
Electrolyte measurement is often carried out using an ion-selective electrode, and the exact design of that electrode plays a role. The two main approaches are the direct ISE and indirect ISE. Each is used extensively, but they do not handle the sample matrix in an identical way.
A direct ISE detects ions in the neat specimen. An indirect ISE assesses ions after dilution, which can introduce small differences related to the fraction of water and proteins in the sample. These differences are typically minor, but they can affect sodium and chloride results to a degree to shift the final anion gap.
Instrument calibration also has a major impact. Even within the same method type, calibration standards, maintenance cycles, and local quality control can influence how the analyzer reads the sample. This is one reason laboratories monitor laboratory reporting closely and use method-specific reference intervals.
The practical implication is that the anion gap is method-dependent because it inherits all the analytical characteristics of the components used in the formula. A small shift in sodium or chloride can look insignificant on paper, but because the formula subtracts two values from sodium, the effect can be magnified.
What Ions Drive the Discrepancy?
3 measurements drive most differences in the anion gap: serum sodium, chloride level, and bicarbonate concentration. Among these, chloride is often the most important driver of assay-related differences because even minor changes in chloride measurement can change the calculated gap significantly.
Serum bicarbonate can also influence the result. Since bicarbonate is subtracted along with chloride, a small analytical or specimen-related change can modify the output. If bicarbonate is measured on a chemistry platform rather than a blood gas analyzer, the result may reflect varied processing conditions or specimen type, which can impact the final number.
Sodium concentration matters as well, especially when different analyzers use different measurement techniques. If sodium trends slightly higher or lower on one platform, the gap can move in the same direction even if chloride and bicarbonate are unchanged.
Hyperchloremia is particularly notable because high chloride values can lower the anion gap. If a method reads chloride a bit higher than another method, the calculated gap may look deceptively low. That is why clinicians should consider whether the result reflects a true physiologic change or a technique-related shift in electrolyte measurement.
Why Does Albumin Alter Anion Gap Reading
Albumin serves as one of the most important unmeasured anions in the body. When albumin is low, the anion gap can appear lower than expected even if acid-base physiology has not changed dramatically. This is why the albumin-corrected anion gap is often applied to improve interpretation.
The corrected value aids account for a low-protein state that would otherwise hide an elevated gap. In practice, this is helpful because the raw result may fall inside the reference interval even when there is a clinically relevant acid accumulation. An albumin correction can show a more accurate picture of the patient’s acid-base disorders.
That said, the corrected gap is still a derived estimate. It does not replace clinical judgment, and it does not eliminate all method-related differences. It simply adjusts interpretation for a major biological factor. When albumin is abnormal, the corrected gap is often more informative than the uncorrected value, but the laboratory method still matters.
Because of this overlap between biological and analytical effects, clinicians should interpret the anion gap in context rather than using one fixed cutoff for every situation. The albumin-corrected anion gap can be especially useful when the result is borderline or when the patient’s acid-base picture does not align with the uncorrected number.
When a Technique-Related Difference Is Significant From a Clinical Standpoint
With modern analyzers, many method-related discrepancies are minimal. But, small does not always mean unimportant. If two instruments differ by several mEq/L, the difference may change whether a result is reported as within range or out of range, especially when the value is close to the threshold.
This becomes most relevant when the goal is precise diagnosis. For example, a borderline elevation might prompt further evaluation for metabolic acidosis, toxic ingestion, or renal impairment. If the result is technique-dependent, the clinician must decide whether the change is real or due to analytic method.
In general, greater differences are more meaningful than small changes. But even slight changes can influence trending over time, particularly when a patient’s labs are being followed across different instruments or different lab systems. The same patient may appear to “change” simply because the analyzer changed.
For that reason, the safest approach is to assess numbers from the same method whenever possible. If a lab changes platforms, users should expect some discontinuity in the anion gap and related electrolytes. The key question is whether the shift changes clinical significance or is merely an expected lab-based difference.
Using an Anion Gap Calculator Safely
An Anion Gap Calculator helps for rapid calculations, but it should be applied with attention of laboratory reporting practices. Before inputting values, confirm that the inputs match the correct sample and the correct reporting units. The calculator is only as accurate as the values input into it.
Take note of specimen type. Serum, plasma, and blood gas samples may not always yield identical bicarbonate values, and some laboratories report chemistry bicarbonate while others rely on https://anotepad.com/notes/97cbgct9 different measurement workflows. If the specimen type changes, the interpretation may change too.
It is also useful to know whether the laboratory uses direct or indirect ion measurement and whether the reported anion gap is based on a specific local reference interval. A calculator can do the arithmetic, but it cannot account for every nuance in the lab method or analyzer configuration.
For the best interpretation, use the calculator as a component of a broader review:
- Check sodium, chloride, and bicarbonate values. See if albumin is low and think about a corrected gap. Review the local reference range and analyzer method. Read the number alongside symptoms, medications, and acid-base status.
This method improves diagnostic accuracy and reduces overreaction to small method-related changes.
Common Pitfalls and Misreads
One common pitfall is assuming that every change in the anion gap reflects a real physiologic shift. In reality, analytical variation and interlaboratory differences can explain some of the movement. If a patient’s labs come from different systems, a small discrepancy may reflect the measurement technique rather than the disease process.
Another frequent issue is the effect of normal saline. Large-volume saline administration can increase chloride and lead to hyperchloremia, which may reduce the anion gap. This is not a calculator error; it is a physiologic and treatment-related effect that can influence acid-base interpretation.
It can also be easy to read too much into a single value without considering albumin. A low albumin level can conceal an elevated gap, and overlooking a corrected gap can lead to missed acid-base disorders. Likewise, a normal result does not always exclude pathology if the method, specimen type, or reporting rules differ from prior measurements.
The most important habit is to ask whether the finding is clinically significant. A slight shift may have little meaning if the overall picture is stable. But a larger shift, especially one that aligns with symptoms or changing bicarbonate, may be highly relevant.
In short, the anion gap is useful, but it is not immune to method effects. Being aware of lab method, analyzer type, and reporting context improves interpretation and helps prevent misreads.
FAQ
Does the anion gap change depending on the laboratory method used?
Yes, it can. The anion gap can change depending on the lab method because different analyzers, calibration processes, and electrolyte measurement techniques can produce slightly different sodium, chloride, and bicarbonate values. These minor variations can alter the final calculation and affect interpretation.
Why do direct and indirect ISE methods affect electrolyte results differently?
Direct ISE assesses ions in an undiluted sample, while indirect ISE measures after dilution. That difference can create method-related shifts in sodium and chloride values, especially when the sample matrix differs. Since the anion gap depends on those electrolytes, the final result may vary.
Should the anion gap be corrected for albumin every time?
Not every time, but albumin should be considered whenever it is abnormal or when the anion gap does not match the clinical picture. The albumin-corrected anion gap can improve interpretation, especially in patients with suspected acid-base disorders or low protein states.
What is a normal anion gap range, and does it vary by lab?
The normal range for the anion gap can differ by laboratory because the reference interval depends on the analyzer, measurement technique, and reporting method. Always use the laboratory’s stated reference range rather than relying on a single universal cutoff.
Can an anion gap calculator replace clinical judgment in acid-base interpretation?
Nope. An Anion Gap Calculator is useful for fast calculation, but it cannot replace medical judgment. Evaluation should include albumin, specimen type, laboratory reporting details, and the full acid-base status. The calculator supports decision making, but it does not provide the diagnosis by itself.