What Is an Anion Gap?
The anion gap is a computed value used to assess acid-base disorders and general electrolyte balance. It comes from routine serum electrolytes and shows the relationship between measured positively charged ions and negatively charged ions in the blood. In most cases, the calculation uses sodium, chloride, and bicarbonate.
A basic way to think about the anion gap is that it estimates the https://anion-gap-chart604.readspirex.com/posts/what-is-the-normal-anion-gap-for-children amount of “unmeasured” ions in the serum chemistry. Those unmeasured ions can increase when acids build up in the body, which is why the anion gap has an important interpretive value in identifying metabolic acidosis.
The standard calculation formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
This calculation is not a direct laboratory measurement. It is a derived number based on laboratory measurement values from an electrolyte panel. Because of that, the result should always be considered with the patient’s broader clinical context in mind.
The anion gap can point toward a high anion gap problem, a normal anion gap pattern, or a mixed disturbance. That makes it a helpful part of clinical decision-making when reviewing acid-base status.
How an Anion Gap Calculator Works
An Anion Gap Calculator is a tool that calculates with the formula automatically once the needed laboratory values are entered. Most calculators prompt for serum electrolytes such as sodium, chloride, and bicarbonate, and some also allow an albumin value so the result can be adjusted.
By organizing the math, an Anion Gap Calculator helps limit manual errors and aids faster acid-base interpretation. It is especially useful in urgent settings where a quick read on metabolic disturbance may guide next steps.
The value of the calculator is not just speed. It also improves diagnostic accuracy by making the process more reliable. Since the anion gap is affected by several variables, a calculator can help clinicians notice whether the result reflects a true anion deficit or whether it is being affected by changes in albumin.
Some calculators display a standard result, while others provide an albumin-adjusted version. That distinction makes a difference because albumin is a major unmeasured anion in blood and can shift the apparent gap. If albumin is low, the unadjusted number may look reassuring even when there is a real acid load present.
In practice, an Anion Gap Calculator is best used as part of a larger assessment that includes the electrolyte panel, a blood gas or arterial blood gas when appropriate, and the patient’s symptoms, history, and exposure risks.
What Is the Uncorrected Anion Gap Mean?
The uncorrected anion gap is the raw value from the equation, without correcting for albumin. It represents the measured difference between sodium and the sum of chloride and bicarbonate, but it does not account for changes in protein binding or shifts in the body’s unmeasured ions.
This number is useful, but it has limits. Because albumin carries a negative charge, lower albumin can decrease the apparent gap even when an acid-base problem is present. In other words, a normal uncorrected result does not always mean the acid-base picture is truly normal.
The uncorrected anion gap still provides important clues about electrolyte balance and can suggest whether acids such as lactate or ketones may be contributing to a metabolic acidosis. However, it should not be interpreted in isolation. It is a screening number, not a full diagnosis.
Knowing the uncorrected value is important because it forms the baseline for comparison. Once you know the raw result, you can decide whether albumin correction is needed to avoid missing a hidden acidosis.
What Is Adjusted Anion Gap?
The modified anion gap is the anion gap after albumin correction has been applied. This modification tries to account for hypoalbuminemia, which can make the uncorrected result appear lower than expected.
Because albumin contributes significantly to the body’s unmeasured anions, the corrected number often gives a more accurate picture of acid-base status. This is especially important when the goal is better interpretation of whether the patient has a true high-gap process.
In many clinical settings, corrected values provide better insight into the real burden of acid accumulation. The corrected anion gap is therefore more useful when you are trying to identify hidden acidosis or estimate the degree of metabolic acidosis more precisely.
The exact correction method may vary by calculator or institutional practice, but the concept is consistent: adjust the gap upward when albumin is low. That makes the result more albumin-corrected and improves the chance of spotting clinically important abnormalities.
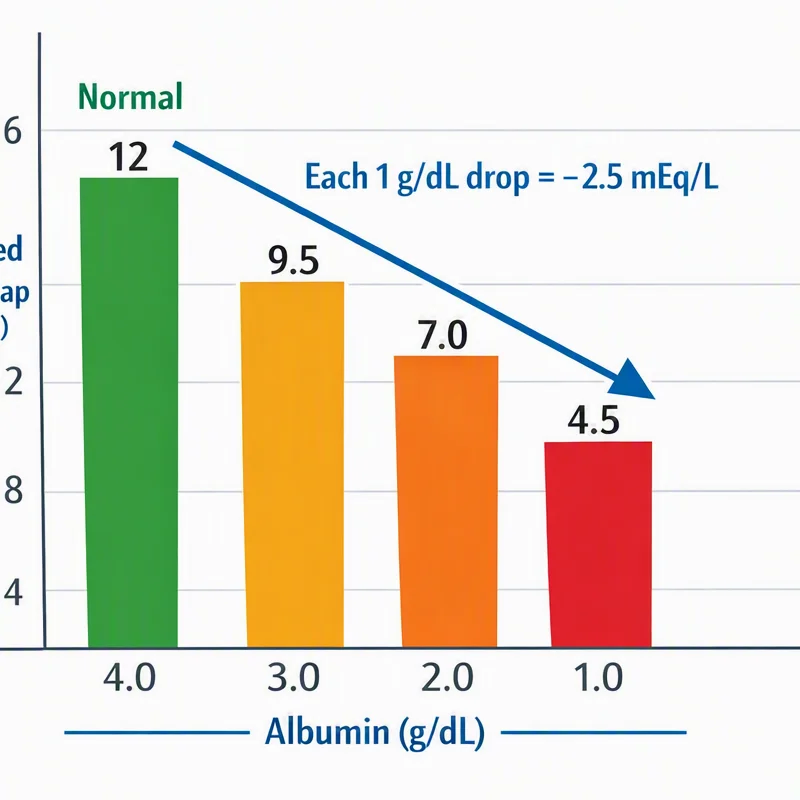
Corrected values are especially relevant in patients with chronic illness, malnutrition, inflammation, or fluid shifts, where hypoalbuminemia is common. In those cases, the corrected anion gap can change the interpretation from “normal” to “abnormal,” which can strongly affect management.
Uncorrected vs Corrected Anion Gap: Key Differences
The key distinction between the two values is whether the result accounts for albumin. The uncorrected anion gap is the original result, while the corrected anion gap is recalculated to enhance diagnostic accuracy.
A normal anion gap on the uncorrected result may still overlook a true high anion gap process if albumin is low. This is one reason the corrected value has more interpretive value in difficult cases. The correction can reveal a larger acid load that was masked by reduced protein binding in the blood.
Both values can be useful, but they solve slightly different questions. The uncorrected result shows the direct output from the serum electrolytes. The corrected result asks what the gap would look like after accounting for low albumin, which may better indicate the underlying pathophysiology.
From a practical standpoint, the corrected number often improves risk stratification. It can help distinguish a benign-looking number from a clinically meaningful acid-base problem. That makes it valuable in assessing metabolic acidosis and guiding next steps in evaluation.
Below is the simplest way to think about it:
- Uncorrected anion gap: basic calculated value from sodium, chloride, and bicarbonate. Corrected anion gap: modified value that accounts for low albumin. Clinical impact: corrected values may identify a missed acid-base disorder.
In short, the corrected version often gives better diagnostic accuracy, while the uncorrected version remains the baseline for evaluation.
When Should the Anion Gap Be Corrected?
Recalculation is most critical when low albumin is available or suspected. Since albumin is a key unmeasured anion, low levels can reduce the apparent gap and hide a real abnormality. This is why albumin correction is a key step in some forms of acid-base interpretation.
It is particularly helpful in critical illness, where albumin often falls due to inflammation, fluid resuscitation, poor nutrition, or organ dysfunction. In those settings, the uncorrected value may understate the severity of the acid-base problem.
Correction also plays a role in kidney disease. Changes in clearance, electrolyte handling, and acid excretion can produce complex results, and the corrected anion gap may help determine whether the patient has a concealed high-gap process.
Another important scenario is lactic acidosis. If lactate is high and albumin is low, the uncorrected gap may not reveal the full extent of the problem. In that case, a corrected number can better capture the actual metabolic burden.
In general, correction should be thought about whenever there is reason to suspect that the measured gap is being altered by changed protein levels rather than true normalization of acid balance.
Interpreting Results Safely and Accurately
Safe acid-base assessment relies on several factors. A result from an Anion Gap Calculator needs to be considered with the patient’s symptoms, the blood gas, anion gap in chronic kidney disease and the electrolyte panel. That complete view reduces the risk of missing or missing a disorder.
To begin, check if the result matches the clinical context. If the patient is unwell, hypotensive, hypoxic, or at risk for toxin exposure, the anion gap may point toward a major metabolic issue even if the uncorrected number is only mildly abnormal.
Next, check whether albumin is low. If so, read the uncorrected value cautiously and consider whether the corrected result alters the picture. This is where the calculator’s interpretive value becomes especially useful.
After that, compare the anion gap with the blood gas pattern. A pH change, bicarbonate shift, or respiratory compensation pattern on an arterial blood gas can show whether a metabolic acidosis is present and whether compensation is adequate.
Lastly, remember that a single number does not explain all acid-base imbalances. Mixed disorders are frequent, and a normal anion gap does not automatically mean that acid accumulation is absent. Clinical judgment continues to be essential for effective clinical decision-making.
Frequent Causes of an Abnormal Anion Gap
An abnormal anion gap can reflect many causes, but several are especially notable because they are associated with metabolic acidosis.
- Ketoacidosis: Accumulated acid from ketone production can elevate the gap and suggest a dangerous metabolic state. Lactic acidosis: Elevated lactate is a common cause of high-gap acidosis and may indicate poor tissue oxygenation or impaired metabolism. Renal failure: Reduced acid excretion and retained organic acids can increase the gap as kidney function declines. Toxins: Certain ingestions can cause an unexpected high anion gap and require urgent recognition.
These causes often produce a high anion gap, but not every serious acid-base problem fits neatly into that category. A normal anion gap pattern can also occur in metabolic disorders, especially when bicarbonate loss is offset by chloride retention. That is why the full interpretation is important.
When reviewing abnormal results, think in terms of pathophysiology. Ask whether the issue is increased acid production, reduced acid clearance, loss of bicarbonate, or a combination of factors. This approach strengthens the quality of the final assessment and supports more accurate risk stratification.
FAQs About Corrected and Uncorrected Anion Gap
What is the difference between uncorrected and corrected anion gap?
The uncorrected anion gap is the raw calculation from sodium, chloride, and bicarbonate. The corrected anion gap adjusts that value for albumin, which improves interpretation when hypoalbuminemia is present. The corrected result is often more accurate for detecting hidden metabolic problems.
Why do you need to correct the anion gap for albumin?
Albumin is a major unmeasured anion, so low levels can make the gap appear falsely normal or low. Albumin correction helps account for that effect and improves diagnostic accuracy when evaluating acid-base disorders.
When is anion gap correction especially important?
Correction is especially important when low albumin is likely, such as in critical illness, kidney disease, or suspected lactic acidosis. It is also useful when the clinical picture suggests a masked issue despite a normal uncorrected result.
Can a normal uncorrected anion gap still hide acidosis?
Certainly. A normal uncorrected value can still overlook a true acid-base problem if albumin is low. In that case, the corrected result may reveal a high anion gap process and show that a hidden acidosis is present.
How do you interpret an anion gap calculator result?
Read the result in clinical context. Review the serum electrolytes, evaluate the blood gas, and check the albumin level if available. An anion gap calculator is a helpful tool, but final lab interpretation should include the patient’s symptoms, history, and overall acid-base status.